Body contouring procedures have grown immensely in popularity among individuals seeking to refine their physical silhouette and reduce stubborn localized fat deposits. Among these interventions, surgical suction-assisted lipectomy remains a gold standard for reshaping aesthetic contours. However, a widespread misconception persists regarding the nature of abdominal fullness: many individuals assume that a distended or enlarged abdomen is caused solely by excess fat residing directly beneath the skin. From an internal medicine and digestive health perspective, central abdominal volume is composed of two distinct biological fat depots—subcutaneous adipose tissue and intra-abdominal visceral adipose tissue. Because surgical body sculpting targets only superficial layers, consulting a gastroenterologist in dubai before opting for liposuction provides crucial clinical clarity regarding metabolic health, internal organ fat storage, and realistic anatomical outcomes.
Understanding Adipose Architecture: Subcutaneous versus Visceral Fat
To understand the anatomical boundaries of aesthetic procedures, one must differentiate between the two primary types of adipose tissue present in the human trunk:
1. Subcutaneous Adipose Tissue (SAT)
Subcutaneous fat resides above the abdominal wall fascia and directly beneath the dermis. It is superficial, soft to the touch, and can be easily pinched between the fingers. Subcutaneous adipose serves as energy storage and thermal insulation. Because it sits entirely outside the muscular abdominal wall, it is accessible to surgical suction cannulas.
2. Visceral Adipose Tissue (VAT)
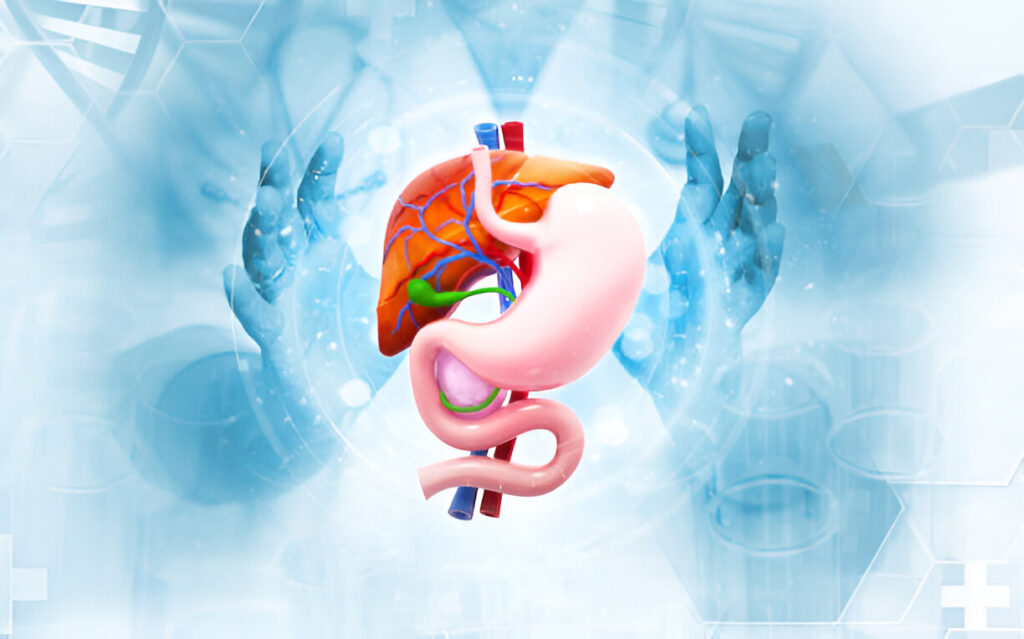
Visceral fat, often referred to as intra-abdominal fat, lies deep beneath the rectus abdominis muscle layer. It wraps around vital digestive organs, including the stomach, liver, pancreas, intestines, and mesenteric tissues. Unlike subcutaneous fat, visceral adipose tissue cannot be pinched from the outside; instead, high levels of intra-abdominal fat push the muscular wall outward, giving the abdomen a firm, rounded, or protruded appearance.
Because visceral fat is located deep within the peritoneal cavity surrounding major blood vessels and internal organs, it cannot be safely accessed or removed via surgical suction. Attempting to address intra-abdominal volume with superficial surgical procedures is anatomically impossible and medically unsafe.
The Metabolic Implications of Visceral Adiposity
Visceral fat is not merely an inert storehouse for excess calories; it is an active endocrine organ that secretes inflammatory cytokines, free fatty acids, and hormones directly into the hepatic portal vein. This portal circulation carries visceral secretions straight to the liver, leading to significant metabolic dysfunction.
Clinical evaluation by a gastroenterologist in dubai frequently identifies metabolic conditions linked to elevated visceral fat, including:
- Non-Alcoholic Fatty Liver Disease (NAFLD) / Metabolic Dysfunction-Associated Steatohepatitis (MASH): Excessive visceral adiposity leads to the accumulation of triglycerides inside hepatocytes (liver cells), causing hepatic steatosis, localized cellular inflammation, and potential progressive fibrosis.
- Insulin Resistance and Type 2 Diabetes: Pro-inflammatory signals released by visceral adipocytes impair systemic insulin receptor sensitivity, leading to chronic hyperglycemia and elevated pancreatic insulin output.
- Systemic Endothelial Inflammation: Visceral fat produces tumor necrosis factor-alpha (TNF-α) and interleukin-6 (IL-6), which elevate systemic cardiovascular and metabolic disease risks.
Removing superficial subcutaneous fat through body contouring does not alter these internal metabolic risks. Studies have consistently demonstrated that removing subcutaneous adipose tissue via suction-assisted lipectomy does not improve insulin sensitivity, lipid profiles, or systemic inflammatory markers because the underlying visceral fat depot remains untouched.
Diagnostic Workup and Intra-Abdominal Assessment
When patients present with central abdominal protrusion, a comprehensive diagnostic workup helps determine the precise ratio of internal organ fat to superficial tissue. Specialized digestive health evaluations utilize non-invasive tools to assess the peritoneal cavity:
| Diagnostic Tool | Clinical Purpose | Structural Insights Provided |
| Abdominal Ultrasonography | Evaluates organ structure and fat distribution. | Identifies hepatic steatosis, gallstones, and subclinical visceral fat thickness. |
| Transient Elastography (FibroScan) | Measures liver stiffness and controlled attenuation parameter (CAP). | Quantifies the exact percentage of fat accumulation within liver tissue and screens for fibrosis. |
| Computed Tomography (CT) / MRI | Provides cross-sectional anatomical mapping. | Accurately calculates the square-centimeter ratio of visceral to subcutaneous fat. |
| Comprehensive Metabolic & Liver Panels | Measures serum transaminases (ALT, AST), lipid profiles, and HbA1c. | Assesses subclinical organ inflammation and metabolic health baselines. |
Identifying high visceral fat or liver steatosis prior to scheduling aesthetic surgeries ensures that underlying metabolic conditions are managed appropriately, reducing surgical risks and supporting overall digestive health.
Addressing Gastrointestinal Causes of Abdominal Distension
In many cases, what appears to be excess abdominal fat is actually exacerbated by functional digestive disorders. Treating subcutaneous tissue while ignoring intra-abdominal gastrointestinal dysfunction yields disappointing cosmetic and physical results.
Common digestive causes of abdominal distension include:
- Chronic Intestinal Motility Slowing and Constipation: Retained fecal matter and gas cause physical expansion of the large intestine, distending the abdominal wall.
- Small Intestinal Bacterial Overgrowth (SIBO): Excessive bacterial colonization in the small intestine leads to rapid fermentation of carbohydrates, creating excessive gas, bloating, and pronounced abdominal swelling that fluctuates throughout the day.
- Food Intolerances and Inflammatory Bowel Conditions: Subclinical inflammation and malabsorption cause fluid retention and bowel loop distension.
A targeted gastrointestinal evaluation resolves these functional complaints through medical management, dietary modifications, and gut microbiome optimization, significantly reducing abdominal girth naturally before any surgical decisions are finalized.
Integrated Care for Sustainable Health Outcomes
Aesthetic body sculpting yields excellent outcomes when performed on candidate patients with localized subcutaneous deposits and firm abdominal muscle tone. However, for individuals whose abdominal volume is largely driven by visceral fat storage or internal gastrointestinal issues, relying on surgical intervention alone can lead to unsatisfactory results.
Consulting a digestive disease specialist allows patients to adopt evidence-based lifestyle, nutritional, and medical interventions designed to reduce intra-abdominal fat stores, reverse hepatic steatosis, and optimize gut function. Combining internal metabolic management with appropriate cosmetic consultations ensures that patients achieve true physical well-being, structural safety, and sustainable long-term health.